Showing posts with label research. Show all posts

Monday, March 09, 2026

CHDI chief scientist: ‘at the precipice’ of treatments, Huntington’s disease community must ‘persevere’ through the stress


As researchers have hypothesized that lowering (reducing) the amount of abnormal huntingtin protein in the brains of people afflicted with Huntington’s disease hits at the root causes of the disease, leading companies have sought to develop drugs in response, like uniQure’s AMT-130 gene therapy.


The huntingtin-lowering approach has become central to the search for disease-modifying therapies that slow, halt, or reverse the course of HD, a progressive disorder still without a treatment after the discovery of the huntingtin gene in 1993.


"We have multiple shots on goal in the huntington-lowering arena, things like uniQure, like PTC, like Skyhawk,” Robert Pacifici, Ph.D., chief scientific officer for CHDI Foundation, told me in a video interview on February 27. “While it's true that none of them have made it out the other end with a positive ruling in a pivotal Phase III trial, we're at the precipice of the types of signals that will indicate that there is a clinically meaningful benefit by lowering huntingtin.”


In our interview, Dr. Pacifici gave his customary overview of the CHDI-sponsored 21st HD Therapeutics Conference, held February 23-26 in Palm Springs.


Dr. Robert Pacifici (right), interviewed by Gene Veritas, aka Kenneth P. Serbin, February 27, 2026 (screenshot by Gene Veritas)


In my introduction, I noted that, because “it had a lot of progress,” scientifically this was the most “exciting” of the conferences that I have attended since my first in 2010.


However, I added, “there was stress for us in the HD community about the uniQure gene therapy program” because we were “shocked” at the abrupt backtracking of the U.S. Food and Drug Administration (FDA) on the drug despite its historic efficacy. This prompted two petitions with 48,000-plus signatures. I recalled that “so many of us in the community are still living with the burden of symptoms, including my sister, now disabled.”


Dr. Pacifici agreed that, until the arrival of an effective therapy, the HD community will have “some high degree of hope, but also a high degree of stress, because I think the closer we get, the more stressful it is that we're at the precipice of actually realizing this incredible journey.”


Dr. Pacific urged that people “continue to persevere.”


Watch my full interview with Dr. Pacifici in the video blow. 


A 75-percent slowing of the disease


At the Therapeutics Conference, a uniQure scientist presented an updated analysis of AMT-130 that “supports the validity” of its “efficacy results.”


With uniQure’s announcement last September that AMT-130 had demonstrated a 75 percent slowing in the progression of the disease over a three-year period, the HD community was jubilant (click here and here to read more).


Reports such as the BBC’s optimistically portrayed AMT-130.


HD and uniQure thrust into the national spotlight


Observers and news reports have described the Trump administration’s FDA as dysfunctional and more conservative. After the FDA surprisingly reversed field in November regarding AMT-130, the anxiety and raw tensions over the drug underscored the HD community’s yearning for an effective therapy.


On March 2 uniQure revealed that the FDA declined to accept its request to keep the agency’s original promise, in which the firm could apply for accelerated approval for AMT-130. Instead, the FDA “strongly recommended” that the company conduct a full-blown, Phase III clinical trial (click here to read more).


The controversy over AMT-130 has highlighted the FDA’s rejection of rare-disease drug programs, thrusting HD and uniQure into the national spotlight. Outlets providing coverage have included STAT, The New York Times, Bloomberg, CNN, CNBC, and the The Wall Street Journal.


On March 6 Vinay Prasad, M.D., the controversial head of the division within the FDA charged with evaluating gene therapies like AMT-130, resigned for the second time. While no reason was stated, the Times noted, leaders in the biotech and investor communities had long pressed the White House for his ouster.


Assisting the 60-plus companies involved


Dr. Pacifici told me that he was an “optimist” regarding the “interaction between the companies and the regulators,” who are “scientific people.”


“I truly believe that politics and money and all of the other perverse things that surround us, notwithstanding, that at the end of the day, the truth conquers all,” he said. “I think that they're going to look at the body of data and evidence, and eventually I think they're going to make the very best decision to get things out as quickly and as safely as possible to the patients who so desperately need these treatments.”


Because of the progress with huntingtin-lowering drugs like AMT-130, Dr. Pacifici noted that companies continue to allocate the “significant resources” necessary for Phase III trials.


The feedback from trials has enabled scientists to “hone the next generation of huntingtin-lowering therapies” and to address related questions, he added.


Dr. Pacifici emphasized that CHDI will continue to advise and assist uniQure and all companies seeking to develop HD therapies. More than 60 firms attended the Therapeutics Conference, which had a record attendance of 445.


Other key techniques


The conference also focused on other potential techniques in the search for therapies, such as the splicing of DNA “either to make less of a toxic protein or make more of a protein that is beneficial,” Dr. Pacifici explained.


Several presentations also discussed potential ways of impacting somatic expansion, the tendency of the abnormal huntingtin gene to expand over time to the point where symptoms are triggered.


Dr. Pacifici emphasized the need to intervene in the disease process long before symptoms arise.


“There's a long phase in Huntington's disease where people have the gene, but overtly, to at least the lay eye, look perfectly normal and healthy,” he explained. However, because they carry the genetic expansion, “deleterious things” can already occur, he added.


Another focus included the ongoing study of brain tissue donated by deceased HD-affected individuals, known as post-mortem tissue. This “unbelievably technological marvel of investigations can then look literally cell by cell at those post-mortem brain sections,” Dr. Pacifici explained.


Vast data from Enroll-HD


Dr. Pacifici and I both wore caps from Enroll-HD, the global registry of more than 22,000 affected individuals and relatives.


CHDI runs Enroll-HD, which provides free data to companies seeking to develop therapies.


uniQure’s use of Enroll-HD data as an external comparison for AMT-130 clinical trial participants caused the FDA to oppose the company’s request for an accelerated drug approval.


Dr. Pacifici called Enroll-HD “one of the most remarkable prospective registry trials that's ever been run.”


The Therapeutics Conference included a presentation on Enroll-HD’s whole-genome-sequencing – mapping a person’s entire DNA – of nearly 20,000 of the people in its database. Announced a year ago, this project has already generated 450 terabytes of data.


It has revealed some crucial new clues about the genetics of HD onset: new discoveries about potential modifier genes that slow or hasten the start of the disease.


Scientists learn much about HD from studying so-called animal models of the disease, but, as Dr. Pacifici reminded me, only humans actually get HD.


Enroll-HD safely and non-invasively collects people’s blood, semen, tears, cerebrospinal fluid and DNA and tracks their symptoms, Dr. Padcific said. Enroll-HD thus helps to answer the big question of “how the disease manifests itself in people” over time and how their individual genetics influence the disease.


People’s participation in Enroll-HD “makes a huge difference,” Dr. Pacifici observed, adding that the program is positioned to prepare for future research needs as the field evolves.


The ‘urgent necessity’ for a therapy


On March 5 Amy Gray, the president and CEO of the Huntington's Disease Society of America e-mailed the HD community an update on the controversy involving the FDA, AMT-130, and Enroll-HD.


Gray noted the “urgent necessity” of a disease-modifying treatment. She recalled that Congress had directed the FDA to apply “‘regulatory flexibility’ for rare diseases – tailoring approaches when traditional trials are not feasible or would unduly delay access.”


Gray added that “innovative trial designs” such as Enroll-HD are appropriate when scientifically justified.


“We appreciate uniQure’s stated intent to continue engaging with the FDA,” Gray wrote.


Conquering HD


Like last year, the 2026 meeting had a session on “new enabling technologies and breakthrough science for neurodegenerative diseases.”


“The techniques that people are using would literally have been considered science fiction five years ago,” Dr. Pacifici said.


These included a bioengineered “mini-brain,” using actual human cells, that assembled all of the different broad classes of cell types in the brain, Dr. Pacifici explained.


The mini-brain was developed and presented at the conference by Alice Stanton, Ph.D., of Massachusetts General Hospital and Harvard Medical School.


“We're going to get her to now introduce cells that have the expanded gene and see how that changes so that we could do experiments in a dish instead of in the living organism,” Dr. Pacifici said. "We've got the best, the brightest doing-state-of-the art work."


To fill remaining “gaps” and “solve bottlenecks” on the way to therapies, yet more discoveries will be needed, he added.


With CHDI’s multi-million-dollar resources, the involvement of big companies, and the participation of HD families, “we’re going to conquer this thing,” Dr. Pacifici predicted.


Dr. Alice Stanton presenting her talk on her human "mini-brain" invention (above) and taking questions from the audience (below) (photos by Gene Veritas)


Monday, February 24, 2025

As a ‘biological being,’ I embrace science’s fight against disease


I am a biological being.


This phrase came to me about a decade ago, and I have been hoping to write about its meaning for a long time.


Now, with scientific research at key American institutions such as the National Institutes of Health and university labs under attack from the Trump administration, the phrase resonates with me stronger than ever.


From the time I was hospitalized in 1977 with two herniated discs after shoveling heavy snow through decades of participation in Huntington’s disease research studies, I have been acutely aware of my body as the object of biomedical observation.


Seeing scans of deteriorating HD brains at scientific conferences leaves me deeply worried about the shrinking of my own brain – the inevitable result of the fact that I carry the HD gene.


In March 2022 I observed preliminary data presented by Triplet Therapeutics from SHIELD-HD, a two-year research study of 70 presymptomatic and early-disease-stage carriers of the HD mutation. Triplet aimed to use SHIELD-HD to support plans for a groundbreaking clinical trial to attack a key driver of HD, somatic expansion, the mutant huntingtin gene’s tendency for continued expansion with age. The program was scuttled because the firm folded in October 2022 as it lacked investment funds.


The 2022 SHIELD-HD data showed deterioration in the brains of the gene carriers.


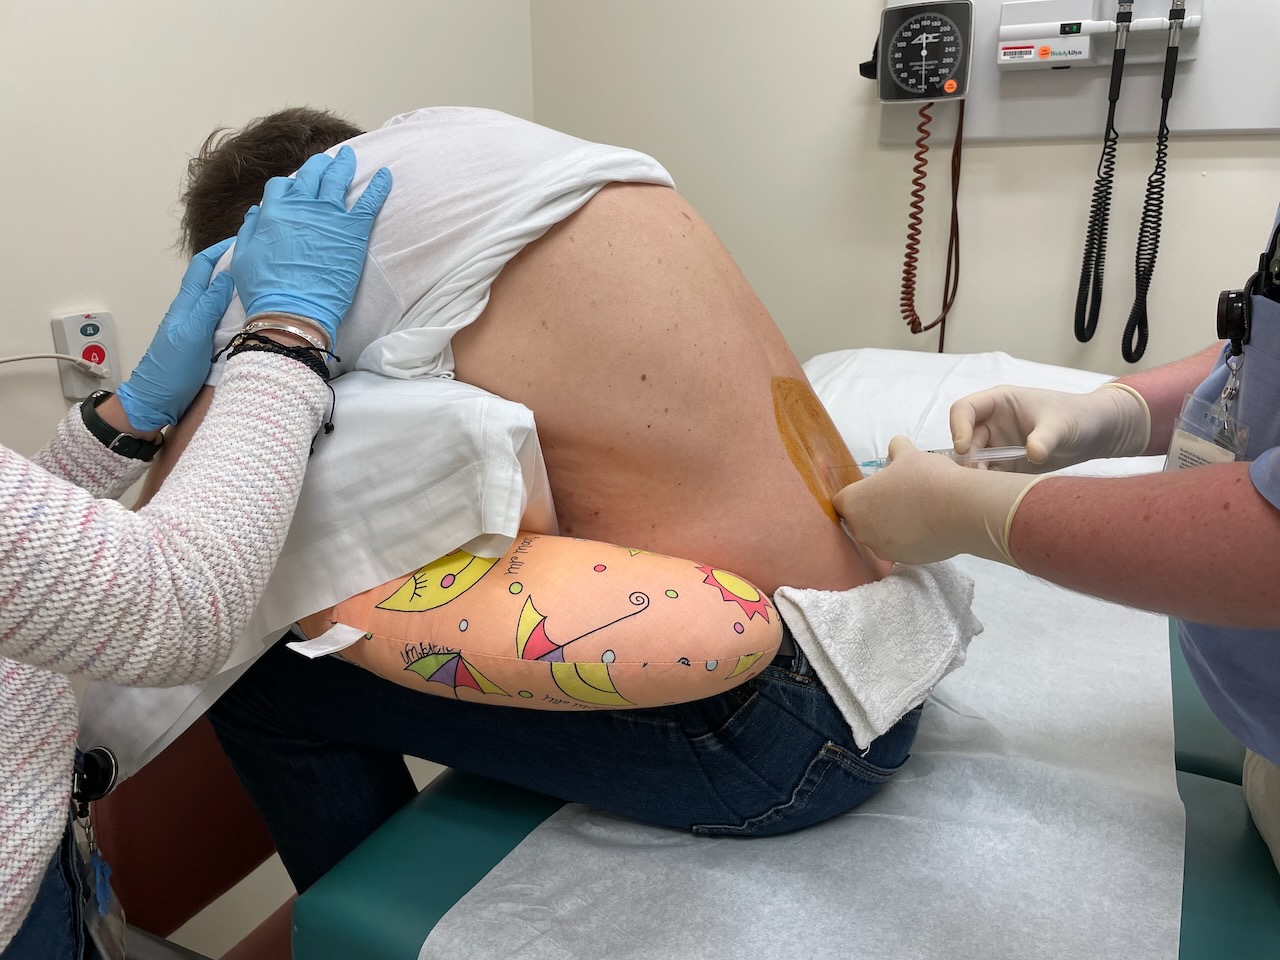
For the first time, I saw information about the impact of the HD gene on my own brain. I had volunteered for SHIELD-HD, undergoing MRI brain scans and cognitive tests and giving samples of blood and my cerebrospinal fluid (CSF) at the HD clinic at the University of California, San Diego.


Below are photos of me in the clinic in August 2022, just two months before the Triplet shutdown. The first shows a neurologist injecting an anesthetic to prepare for the drawing of my CSF. In the second photo the doctor draws a small amount of my CSF. It was the last of my several CSF drawings over the course of SHIELD-HD. Scientists see analysis of CSF, which bathes the brain, as a major tool in the search for therapies for HD. 


Having CSF drawn is a safe procedure but can be painful. Each time I drove home by myself within a couple hours of the drawing. I am very glad I did it.


Analysis of SHIELD-HD


With the end of Triplet, final analysis of the key SHIELD-HD data was completed by CHDI Foundation, Inc., the largest private funder of HD research. The analysis was presented at the 19th Annual HD Therapeutics Conference, sponsored by CHDI, in February 2024.


A future article will further explore my participation in SHIELD-HD and the importance of that program for HD research.


The 20th Therapeutics Conference: a sign of collaboration


As a biological being, I embrace science, not useless conspiracy theories. At the University of San Diego, where I teach and research, I began a new course this month called “A History of the Brain: Examining Huntington’s Disease.” One key lesson from the history of brain science: reliance on superstition was replaced with scientific observation – the key to solving neurodegenerative disorders like HD.


On a large scale, so has the HD community participated in and supported science – from the start of the hunt for the gene in the 1970s to programs today such as Enroll-HD. Tens of thousands of individuals from around the world have taken part, despite the fact that HD is a rare disease, with about 40,000 affected individuals in the U.S.


CHDI, the Huntington’s Disease Society of America, the Hereditary Disease Foundation, Help4HD International, and other HD organizations also rely on science and cooperate with scientific institutions.


A magnificent example of scientific collaboration will take place starting this evening in Palm Springs, CA, as the 20th HD Therapeutics Conference gets under way at the Parker hotel.


Stay tuned for reports about the meeting.

Saturday, January 04, 2025

Savoring 20 years of my Huntington’s disease blog


This month I am celebrating the 20 years of this blog.


I began At Risk for Huntington’s Disease on January 10, 2005, wanting to “squeeze as much life into my days as possible” before experiencing the debilitating HD symptoms that led to my mother’s death a year later. Because I lived in what I called the “terrible and lonely HD closet” – fearful of genetic discrimination – I used the pseudonym “Gene Veritas,” “the truth in my genes.” That name reflected the fact that I had tested positive for the HD gene in 1999.


My mother died at 68, after two decades of debilitating symptoms, which was very painful to watch.


I turned 65 last month. By this age, I had expected to have full-blown HD, which would have left me unable to work, drive, or write.


But, according to my latest neurological checkup, I don’t yet have apparent HD symptoms!


In general, the more abnormal the gene, the earlier the age of disease onset. My mother and I have the same gene mutation, suggesting a similar disease path. However, although my mother’s symptoms started in her late 40s, one or more modifier genes, the functions of which were discovered a decade ago, have perhaps delayed my disease onset.


This article is number 336. Each day of good health is a blessing.


Gene Veritas (aka Kenneth P. Serbin) with his blog (photo by Regina Serbin)


The impact


In 2012, I exited the HD closet by publishing an essay – and using my real name, Kenneth P. Serbin – in The Chronicle of Higher Education. It was titled “Racing Against the Genetic Clock.” Going public opened new vistas of advocacy and enabled me to blog with greater transparency.


In December 2022. I published a detailed analysis of the blog in “Striving for a Realistic and Unapologetic View of Huntington’s Disease” in the Journal of Huntington’s Disease. It described how the blog has helped give voice to the HD community by exploring the major challenges faced by HD families, becoming a key reference for those families, and chronicling the quest to defeat the disorder.


As I observed, the blog has also “helped document the new and harrowing experience of living in the gray zone between a genetic test result and disease onset.”


At Risk for HD has addressed multiple topics including advocacy, caregiving, family trauma, coping strategies, genetic testing, discrimination, leaving the HD closet, participation in research and clinical trials, as well as religion, faith, and spirituality.


When my mother was diagnosed with HD in 1995 – two years after the discovery of the gene – little hope existed for treatments that could slow the progression of HD. However, in the past decade, advances in academic labs and biopharma firms have led to key clinical trials that show potential for affecting the course of HD and perhaps even a cure (click here to read more).


Telling the story of those complex developments has become a major focus of At Risk for HD. With the growing number of research projects, I have necessarily highlighted those that appear closest to producing actual drugs such as the Roche gene silencing program, which I have covered extensively.


In 2021, the first Roche trial showed lack of efficacy. In 2023 Roche started enrolling volunteers in a more focused trial to see if the drug might work at least in some patients. Other key trials are in progress or being planned.


Hoping for an HD-free world, savoring life


Writing the entries of At Risk for HD has given me great meaning and purpose, which researchers have identified as increasing well-being and positively impacting the course of the disease.


For now, I plan to continue blogging as long health permits – and until the quest for a cure is complete.


In February, I hope to attend the crucial 20th Annual HD Therapeutics Conference at the Parker Hotel in Palm Springs, CA. The conference is sponsored by CHDI Foundation, Inc., the largest private funder of HD research.


In 2011, I delivered the conference keynote speech before 250 scientists, physicians, and biopharma reps – a decisive step towards my complete exit from the closet in 2012 and chronicled in this blog.


I have described the conference as the “Super Bowl of HD research,” covered in many blog articles and videos of scientists (see, for example, this one).


With the rest of the HD community, I hope for the announcement of effective treatments. I very much look forward to reporting on progress.


Just as important is the need to savor life – another key lesson of my journey with the HD community, this blog, and my friends and family.

Friday, July 12, 2024

Exploring the unique qualities of INGREZZA, the newest FDA-approved drug for Huntington’s disease chorea


After the news last year that the U.S. Food and Drug Administration (FDA) had approved INGREZZA to treat chorea associated with Huntington’s disease, a debilitating movement disorder, I wanted to better understand the development of this drug and the unique qualities claimed by its creator.


On November 17 I interviewed company officials at Neurocrine Biosciences, Inc., which fashioned valbenazine – the chemical name for INGREZZA – in the early 2000s. In 2017, INGREZZA was approved by the FDA for the treatment of tardive dyskinesia, an irreversible involuntary movement disorder unrelated to HD. Neurocrine is in San Diego, one of the world’s leading biotech hubs and where I reside.


In an initial report on INGREZZA, including a Zoom interview with three Neurocrine officials, I noted the drug’s advantages over the two other FDA-approved chorea remedies, Xenazine (tetrabenazine) and Austedo (deutetrabenazine).


INGREZZA is easier to take, requiring just one daily dose in capsule form. Xenaxine and Austedo have long required multiple daily doses, although in May the FDA approved once-daily extended-release tablets for Austedo. Unlike the other drugs, INGREZZA also does not require titration, that is, slowly increasing the dosage over weeks. INGREZZA is always just one pill.


In contrast with the other drugs aimed at chorea, INGREZZA is a capsule – not a tablet – and is taken once daily even without an extended-release formulation. These characteristics potentially provide physicians and patients greater flexibility in dosing, because INGREZZA can be crushed and is available in three effective doses. As a result, Neurocrine’s drug, while indicated for oral administration, can also be crushed and mixed with food or provided through a feeding tube – often necessities for late-stage HD patients.


In April the FDA approved INGREZZA SPRINKLE capsules, a new formulation of the drug, in oral granules. Neurocrine developed this version of the drug for those with HD or tardive dyskinesia who experience difficulties in swallowing. It can be sprinkled on soft food. INGREZZA SPRINKLE offers the same three simple and effective dosing options (40 mg, 60 mg and 80 mg) as INGREZZA.


In last year’s interview, recognizing that INGREZZA only treats chorea, the Neurocrine officials stated that they plan to seek potential disease-modifying remedies that could potentially slow, halt, or reverse the progression of debilitating neurological conditions, which might include HD.


A substantial reduction in chorea


According to a Neurocrine press release (and also a June 2023 scholarly article in Lancet Neurology), INGREZZA decreased chorea severity three times better than a placebo.


So far researchers have not done a head-to-head study of Xenazine, Austedo, and INGREZZA. All three are VMAT2 inhibitors, designed to reduce involuntary movements of chorea. VMAT2 inhibitors help regulate dopamine, a chemical messenger in the brain that affects movements.


As my above-mentioned article stated, Dietrich Haubenberger, M.D., the executive medical director at Neurocrine and clinical lead for the firm on the successful Phase 3 KINECT-HD clinical trial leading to INGREZZA’s approval, called valbenazine a “unique molecule.”


Comparing INGREZZA with competitors


In 2015 I reported on the key differences between tetrabenazine (Xenazine) and its derivative deutetrabenazine (Austedo), which was also developed in San Diego.


During my November 2023 interview with Dr. Haubenberger and other Neurocrine scientists, I sought to better understand INGREZZA’s uniqueness and its benefits for HD-affected individuals. How does valbenazine contrast with tetrabenazine and its derivative deutetrabenazine?


The basics were described by Dimitri Grigoriadis, Ph.D., a pioneer of valbenazine and today a semi-retired distinguished scholar at Neurocrine. A neuropharmacologist by training, Dr. Grigoriadis started with the firm at its inception in 1993 and previously served as chief research officer.


Understanding the chemistry


Dr. Grigoriadis explained how INGREZZA works in the brain.


The “unique part of INGREZZA,” he said, is that it gets broken down by the body, then produces a single “isomer” that is a key metabolite of tetrabenazine. A metabolite results from the breaking down of a chemical.


“That is the chemical that binds to VMAT2, the protein, and blocks the entrance of dopamine” into relevant parts of brain cells, Dr. Grigoriadis added.


The drug discovery that Neurocrine did for valbenazine involved a drug profile that was highly selective for the VMAT2 protein, Dr. Grigoriadis recalled. “And through our research, we were able to identify a molecule that provides only the high affinity, very selective isomer of [the metabolites] of tetrabenazine.”


Comparing hands


Dr. Grigoriadis illustrated the concept of an isomer by noting how left and right hands resemble each other but are positioned differently.


“An isomer is a molecule that is exactly the same, has the same structural components,” he said. “So, it's an identical molecule, but it's left-handed, right-handed orientation. Your hands are four fingers and a thumb. They're identical, but they are in a different orientation.”


Isomers work in a similar way, he continued.


“They fit differently,” he said. “Functionally, they are different, even though they look exactly the same. You could have two isomers of the same molecule, a left hand and a right hand, that fit into different proteins, that fit into different spaces because they are in a different orientation.”


As a result, the various qualities of a drug “could be different,” he continued, resulting in a “slightly different” way in which the chemicals produced by INGREZZA “function.”


Dimitri Grigoriadis, Ph.D. (left), Dietrich Haubenberger, M.D., and Gene Veritas (aka Kenneth P. Serbin) discuss INGREZZA at the Neurocrine offices (photo by Aimee White, Director, Corporate Communications, Neurocrine). (Click on an image to make it larger.)


Building on tetrabenazine


At the time of valbenazine’s discovery, Neurocrine did not know whether it could help patients with diseases like tardive dyskinesia or HD, because the research on valbenazine had not been done, emphasized Eiry Roberts, M.D., Neurocrine’s chief medical officer. No drug had been developed for tardive dyskinesia before valbenazine.


“So this was a totally new research project,” Dr. Roberts continued. “There were learnings from experience with tetrabenazine that made it important to find out how valbenazine could be a safe and effective treatment for patients with conditions not sufficiently addressed by other medications available at the time.” The company also did extensive research to prove valbenazine’s safety, she added.


In addition, Neurocrine determined that, besides showing promise in the lab and efficacy in clinical trials for the treatment of tardive dyskinesia and chorea associated with Huntington’s disease, valbenazine could be mass-produced, Dr. Grigoriadis said.


Benefits for patients


Dr. Haubenberger stressed that INGREZZA is unique because  it involves just “one capsule, once daily with no complex dose adjustments to get to an effective dose.”


The once-a-day quality results from valbenazine’s “very long half-life of its effectiveness” (the time it remains in the body), explained Grace Liang, M.D., a movement disorders neurologist and Neurocrine’s vice president of clinical development in neurology.


“We know that the long half-life is important not only for the convenience this provides, but it allows patients to take it consistently without forgetting a dose,” said Dr. Liang. “Everybody has a life to live.” The “long duration” in the body and the selectivity – that it doesn’t act on other receptors of the brain that may cause other effects – make INGREZZA “special” for patients, she added.


INGREZZA “gives that nice, smooth, and steady coverage,” in contrast with the other chorea drugs, which have multiple daily doses and a shorter half-life, Dr. Liang continued.


INGREZZA also takes effect faster than Xenazine and Austedo, Dr. Haubenberger pointed out. He added that “with the first dose and as early as at two weeks of treatment, the clinical trial showed a greater reduction of chorea in patients on valbenazine compared to placebo.”


Unlike medicines that purposely have a material on their capsule to cause an extended release, valbenazine needs no such modification to achieve its “inherent,” smooth, once-daily effect, Dr. Roberts added.


Looking to the HD community


The FDA approved INGREZZA for use in adults with HD chorea. Neurocrine has no plans for a clinical trial of the drug in juvenile HD patients.


“We do recommend that people just use INGREZZA as it's labeled,” Dr. Liang said. “Obviously the care providers, the physicians would need to evaluate what the best treatment options are for those children, and we're hopeful that future developments can also support their needs as well.”


“Data is still being collected,” said Dr. Haubenberger, referring to an ongoing three-year study of more than 150 adults with HD taking INGREZZA. “There's lots more to learn about the compound itself and that's really where we want to invest in, where we can even learn more, share that with the community and even learn from that to inspire future avenues of research in HD and also other conditions.”


In these studies that reflect more “real-life settings, there’s much that can be learned from a broader data set than what could feasibly be done in a controlled clinical trial,” added Dr. Liang.


Other valbenazine projects


Previously, a Neurocrine clinical trial program of valbenazine for Tourette’s disorder did not show efficacy, Dr. Roberts said.


Neurocrine currently has a Phase 3 program for “valbenazine as an adjunctive treatment for schizophrenia, adjunctive to the antipsychotics that those patients take right now,” Dr. Roberts said. The drug is also in a Phase 3 study for the “commonest movement disorder in children, dyskinetic cerebral palsy,” she added.


In March Neurocrine announced the start of a Phase 1 clinical trial with their next-generation VMAT2 inhibitor, NBI-1065890, to study the safety and tolerability in healthy volunteers.


“We’re excited to bring this next-generation, internally discovered, highly potent, oral, selective VMAT2 inhibitor into the clinic with the hope of providing differentiated benefit in treating certain neurological and neuropsychiatric conditions,” Dr. Roberts stated in a press release. 


Gene Veritas (left) with Eiry Roberts, M.D., Chief Medical Officer, Neurocrine (photo by Aimee White, Neurocrine)


Aiming for disease-modifying therapies


Our November interview concluded with Dr. Roberts’ reflections on Neurocrine’s commitment to seek disease-modifying therapies for neurological conditions such as HD, including its new partnership with Voyager Therapeutics, a key player in the development of next-generation gene therapies. Voyager has experience in HD research.


“While symptomatic treatments are incredibly important for patients living with the diseases that we're seeking to serve, like Huntington's, for us to be a true innovator as well in this field, we need to be focused on understanding disease modification and cures,” Dr. Roberts said. “And so the collaboration with Voyager is one that gets us into the gene therapy space for potential curative or disease-modifying treatments. And we have other efforts that are very early in our research to look at different ways of coming upon disease modification.”


“It's really a focus area for us as we look at some of these novel platforms that we're coming forward with,” Dr. Roberts concluded.


Those research platforms are getting a boost: Neurocrine is moving to a new, state-of-the art 535,000-square-foot research campus. The lab space is scheduled for completion by year’s end.


Neurocrine's new research campus (photo courtesy of Neurocrine).